Showing posts with label Circumcision. Show all posts

Monday, March 5, 2012

The Boy Who Was Raised As A Girl - Botched Circumcision

You thought I was finished, didn't you?  I don't think I will ever be finished on this subject until not one boy in the world is forced to undergo this brutal and unnecessary operation.   I want to share with you a story that made me weep, and grind my teeth with fury, and made me want a gun.  It still makes me weep.   I apologise if the print is blurry, it will be from tears. I do urge you to read it, as it isn't a one-off as far as circumcision horror stories go, and the 'accidents' are still happening to this day. One accident is one too many.

In 1965 in Winnipeg, (Canada) a young couple had twin boys whom they named Brian and Bruce.  When the twins were around six or seven months old, their mother took them to the doctor, as they were having trouble urinating.  The twins were diagnosed with phimosis, and then given a referral for circumcision.   This procedure was carried out on Bruce on 27th April, 1966 by a urologist.  For some unknown reason, the urologist used cauterisation to remove the foreskin, and not a scalpel.  Something went radically wrong during the procedure, and most of the baby's penis was burned off.   There was far too much damage to the penis for it to be repaired surgically.   

Not unsurprisingly, baby Brian's operation was cancelled.  His phimosis corrected itself, as is most often the case. 

The newborn twins with proud mother

Baby Bruce's parents, obviously extremely distressed and worried for their child's future, consulted with many doctors, searching for help for their child.  All agreed there was little hope for repair.   Then, the Reimers saw a television program about an American psychologist, and his theories on sex and gender. Dr. John Money of Johns Hopkins University in Baltimore was developing a reputation as a pioneer in the field of sexual development and  gender identity.  This was based on his work with "intersex" patients.

"Money was a prominent proponent of the 'theory of Gender Neutrality'; that gender identity developed primarily as a result of social learning from early childhood and could be changed with the appropriate behavioural interventions. The Reimers had seen Money being interviewed on the Canadian news program "This Hour Has Seven Days", where he discussed his theories about gender. He and other physicians working with young children born with abnormal genitalia believed that a penis could not be replaced but that a functional vagina could be constructed surgically, and that he would be more likely to achieve successful, functional sexual maturation as a girl than as a boy." (From Wikipedia)

Bruce's parents were convinced by Money and others that this was the best hope for their son, and thus when Bruce was 22 months old, an "orchidectomy" (surgery to remove a testicle/testicles and the full spermatic cord, through an incision in the abdomen. Orchidectomy is one form of castration) was performed on the little boy.  Bruce was then  renamed 'Brenda', and was to be raised as a girl.  John Money must have been ecstatic at this 'gender reassignment' - he had just been handed the perfect control couple in Bruce and his twin Brian.

"Brenda"
 
"What remained of his penis was left, not to interfere with his urinary tract. When Bruce was released from hospital, his parents were told to raise him as a girl. The family was told not to divulge anything to anyone. They went home with a girl they called Brenda.
"We relatively quickly came to accept that," Janet Reimer told CBC News in 1997. "He was a beautiful little girl."   (From CBC News Indepth)

"This reassignment was considered an especially valid test case of the social learning concept of gender identity for two reasons. First, Reimer's twin brother, Brian, made an ideal control since the two not only shared genes and family environments but had shared the intrauterine environment as well. Second, this was reputed to be the first reassignment and reconstruction performed on a male infant who had no abnormality of prenatal or early postnatal sexual differentiation."   (From Wikipedia)

Over the course of the next 10 years Money provided "psychological support" and saw 'Brenda' annually to assess the outcome of his case.

For some years, Money reported on Reimer's progress, referring to him as the  "John/Joan case". He reported successful female gender development, and he used Bruce's case as  support for the feasibility of sexual reassignment and surgical reconstruction -  even in non-intersex cases. He  reported -  "The child's behaviour is so clearly that of an active little girl and so different from the boyish ways of her twin brother."   He stated that the twins were happy in their assigned roles. Brian a rough and tumble boy, his sister Brenda a happy little girl. Money was featured in Time magazine and included a chapter on the twins in his famous textbook Man & Woman, Boy & Girl

However, in notes by a former student at Money's laboratory, it states that during the follow-up visits, which occurred only once a year, Reimer's parents routinely lied to lab staff about the success of the experiment.

From the first, 'Brenda' refused and was confused by her so-called gender, and was bullied and relentlessly teased at school for her masculine walk, behaviour and tastes and was called names such as 'it',  'freak', and 'caveman'.   At the age of only 2, 'Brenda' angrily tore off her dresses. She refused to play with dolls, she would beat up her brother, and take his toy cars and guns. She complained to both her parents and her teachers that she felt like a boy.  Because of Dr. Money's strict orders of secrecy, her parents insisted that she was only going through a phase. Meanwhile, 'Brenda's' guilt-ridden mother attempted suicide, and  her father descended  into alcoholism. Neglected, 'Brenda' eventually descended into drug use, pretty crime, and clinical depression. 

'Brenda's' visits to Money in Baltimore were a traumatic experience, rather than supportive, and when Money began pressuring the family to bring 'Brenda'  for follow-up surgery, during which a vagina would be constructed, the family discontinued the visits. By the age of 13, 'Brenda' had suicidal depression, and told his parents he would commit suicide if they made him see John Money again.   

From Wikipedia: Dr. Money forced the twins to rehearse sexual acts involving "thrusting movements" with (Brenda) playing the bottom role. As a child, Reimer painfully recalled having to get "down on all fours" with his brother, Brian Reimer, "up behind his butt" with "his crotch against" his "buttocks". In another sexual position, Dr. Money forced Reimer to have his "legs spread" with Brian on top. Dr. Money also forced the children to take their "clothes off" and engage in "genital inspections". On at "least one occasion", Dr. Money took a "photograph" of the two children doing these activities. Dr. Money's rationale for these various treatments was his belief that "childhood 'sexual rehearsal play'" was important for a "healthy adult gender identity".

From the age of 22 months through to his teenage years 'Brenda'  urinated through a hole surgeons had placed in the abdomen.  She was given oestrogen during adolescence, in order to induce breast development. Having no contact with the family once the visits were discontinued, John Money published nothing further about the case to suggest that the reassignment had not been successful.

When 'Brenda'  was 13, (the age varies according to the source) his parents finally told him the truth about his gender reassignment, following advice from Reimer's endocrinologist and psychiatrist.  At 14, Reimer decided to assume a male gender identity, calling himself David.

"Bruce Reimer said he had one thought at the time: to go to the hospital and track down and shoot the doctor who had botched his circumcision. In the end, he was unable to exact his revenge, but turned his anger on himself. "   (From CBC News Indepth)

Bruce attempted suicide three times. The third, which was an overdose of tablets, left him in a coma. When he recovered, he started on the long road to a normal life as a man.  By 1997, Reimer had undergone treatment to reverse the reassignment, including testosterone injections, a double mastectomy, and two phalloplasty (penis reconstruction) operations. 

"David soon embarked on the painful process of converting back to his biological sex. A double mastectomy removed the breasts that had grown as a result of oestrogen therapy; multiple operations, involving grafts and plastic prosthesis, created an artificial penis and testicles. Regular testosterone injections masculinized his musculature. Yet David was depressed over what he believed was the impossibility of his ever marrying. " (From "Slate")

He married Jane Fontaine and became a stepfather to her three children. 

"When David was almost 30, he met Dr. Milton Diamond, a psychologist at the University of Hawaii and a long-time rival of Dr. Money. A biologist by training, Diamond had always been curious about the fate of the famous twin, especially after Money mysteriously stopped publishing follow-ups in the late 1970s. Through Diamond, David learned that the supposed success of his sex reassignment had been used to legitimize the widespread use of infant sex change in cases of hermaphroditism and genital injury. Outraged, David agreed to participate in a follow-up by Dr. Diamond, whose myth-shattering paper (co-authored by Dr. Keith Sigmundson) was published in Archives of Pediatrics and Adolescent Medicine in March 1997 and was featured on front pages across the globe."  (From Slate)

Soon after this, David went public with his story.  John Colapinto, in December 1997's "Rolling Stone" magazine, published a widely broadcast and influential account.  David Reimer and John Colapinto then elaborated on David's story, in the book " As Nature Made Him: The Boy Who Was Raised as a Girl".

David's story came to a tragic end in 2004, on 5th May, when he shot himself.  Nobody really seems to know the exact reasons for his suicide, but his brother had committed suicide two years previously, (Brian had schizophrenia), David had become unemployed, he had lost a great deal of money through bad investments, and his wife had asked for a separation. His life as a man was far from peaceful and placid, David had numerous fears, cycles of depression and an explosive temper. 

David Reimer

The Intersex Society of North America, which opposes involuntary sex reassignment, treats the story of David Peter Reimer as a cautionary tale about why the genitals of unconsenting minors should not be needlessly modified. (Wikipedia)


Tuesday, February 21, 2012

Circumcision - I Wouldn't Do It To My Child If You Paid Me - Part Five

I surely hope you aren't fed up with me by now!  Up to last night, we saw that 1. Medical Professions do not advocate routine circumcision for newborns, 2. Circumcision is painful in the extreme and 3.  It is dangerous to administer anaesthetic to very young babies, 4. There are adverse complications and even death associated with circumcision and 5. There is no significant reduction in UTI's for circumcised neonates.

There are many myths about the operation and I am surely not going to cover them all, especially in depth, as it is just too much.  There are a couple of myths that are dangerous ones, and which have recently been disproven and it is these I am going to address here.


The myth that circumcision prevents STD's and HIV-AIDS

World Health Organization (WHO) stated:

There is compelling evidence that male circumcision reduces the risk of heterosexually acquired HIV infection in men by approximately 60%. Three randomised controlled trials have shown that male circumcision provided by well trained health professionals in properly equipped settings is safe. WHO/UNAIDS recommendations emphasise that male circumcision should be considered an efficacious intervention for HIV prevention in countries and regions with heterosexual epidemics, high HIV and low male circumcision prevalence. Male circumcision provides only partial protection, and therefore should be only one element of a comprehensive HIV prevention package which includes: the provision of HIV testing and counselling services; treatment for sexually transmitted infections; the promotion of safer sex practices; the provision of male and female condoms and promotion of their correct and consistent use.

There has been no convicing evidence that the incidence of infection with STDs is reduced by circumcision.  The HIV and STD studies are normally done in poor and under-developed countries, and are not relevant to Australia, UK or USA.

Furthermore, circumcising an infant to reduce the risk of HIV and STDs is not justifiable - infants are not sexually active!
 
Myth - Circumcision prevents penile and cervical cancer

If you are exposed to strains of human papilloma virus through unprotected sex with multiple partners, or you smoke, these are the main risk factors for cervical and penile cancer.   Penile cancer is very extremely rare, there is less than 1 case in 100,000 men, and the median age of diagnosis is 64 years.   Circumcised men do develop cancer of the penis, and this can develop on the scar from the circumcision!  Strangely, breast and testiticular cancer is more common in men than is penile cancer.

From Wiki Commons - Prevalence of Circumcision by country

Myth - Circumcision is necessary to prevent phimosis and paraphimosis

The condition known as phimosis is where the foreskin can't be fully drawn back to uncover the glans.  Almost all infants and young boys have phimosis, which is normal for the infant and juvenile penis.   As discussed previously, the foreskin usually becomes retractable between ages 3 to 13, and nothing need be done unless the child is having discomfort or pain.  Phimosis does not need surgery unless conservative treatment fails.

Paraphimosis is a condition where the retracted foreskin has become stuck behind the glans, and cannot be brought forward again.  Using cold water and gentle compression this problem can usually be remedied.  In rare instances, where the skin is very tight, urgent medical attention is needed.

I do hope I have given a broad outline of the myths about circumcision, and the extremely strange reason why many still insist on circumcising their boys.   One aspect that keeps being dragged up is cleanliness - a good bath or shower with soap is all that is needed for cleanliness and hygeine.  When a boy is old enough he will normally pull back the foreskin and clean around under it himself.  
  
According to advocates of circumcision, there are many health benefits for the infant.  If this is so, if we are circumcising because way in the future this might prevent penile cancer - why then are we not operating on little girls to remove tiny breast buds?  The risk of a woman developing breast cancer is about 12% over her lifetime, which is a much higher risk than a man developing penile cancer.

Strangely enough, "the Australian Institute of Health and Welfare has found that Australian children have become significantly healthier as the incidence of circumcision has declined."  (Circinfo.org)   So much for circumcision having health benefits for the child.

There are psychological factors to consider as well, with circumcising infants - although I have actually seen these brushed aside as being unfounded, and anecdotal.  Of course evidence of psychological harm will be anecdotal - after all, the man is telling us of the harmful effect his circumcision has had on his mental wellbeing.  In a survey reported by Circumcision Information, they state that over 80% of 300 self-selected circumcised men said they had been harmed emotionally by infant circumcision.   Responses showed that at least one of the following feelings were reported:  anger, resentment, rage, hate, revenge, a sense of deficiency or loss, a diminished body image.  Disbelief, confusion, shame, embarrassment, feeling victimised, robbed, cheated, raped, violated, abused, mutilated, deformed.  They experience fear, distrust, withdrawal, sadness, pain and grief.   Some men have commited suicide.   Others have successfully sued for pain and suffering.

And a little fact that horrified me?  We saw before that the prepuce is rich in blood vessels.  This makes it likely to haemorrhage when it is cut.  The frenular artery is also at risk of being cut during the procedure.   An infant has only a very small volume of blood. For example a 4kg baby has only 340ml (or 11.5oz) of total blood at birth.   That is 85ml per kilo of weight.  An infant only needs to lose 68ml (2.3oz - about half a cup - go measure it) and he has lost 20% of his total blood volume - this is about all they can tolerate before hypovolemic shock sets in (shock from blood loss), which is quickly followed by death.  This has happened on many occasions.  A frightening fact is that the volume of blood loss that might kill a baby, which is 85ml, is easily concealed by disposable nappies (diapers).   You would not even know your baby was bleeding to death.

It seems to me that here we are in the year 2012, and for some unfathomable reason we are STILL following the dictates of some half-baked, unscientific and uneducated theory dreamed up by a long-forgotten prudish and sadistic doctor in the early 1800's - to stop men masturbating!   Sheer superstition still rules the day!  We may as well start burning witches again.


The phrase that keeps running through my head is the medical ethic "first, do no harm"  -

Nonmaleficence, which derives from the maxim, is one of the principal precepts of medical ethicsthat all medical students are taught in medical school and is a fundamental principle for emergency medical services around the world. Another way to state it is that "given an existing problem, it may be better not to do something, or even to do nothing, than to risk causing more harm than good." It reminds the physician and other health care providers that they must consider the possible harm that any intervention might do. It is invoked when debating the use of an intervention that carries an obvious risk of harm but a less certain chance of benefit.

Thank you for staying with me on this very long blog. 

Monday, February 20, 2012

Circumcision - I Wouldn't Do It To My Child If You Paid Me - Part Four

Thanks again for reading these blogs!  Not much more to go now, and by the finish I hope you will have gained some understanding about circumcision - I know that when I did my months of research I learned so much.

Back to the myth busting.  So far we have seen that 1. Medical Professions do not advocate routine circumcision for newborns, 2. Circumcision is painful in the extreme and 3.  It is dangerous to administer anaesthetic to very young babies.


The next myth is that circumcision is just a tiny snip and that there are no risks attached.

On the contrary, there are many risks of circumcision - these include infection, bleeding, scarring, excessive skin removal, damage to the glans and frenulum, loss of the penis and even death.   The danger of this myth is that it is more risky to circumcise an infant than an adult, simply because a baby's penis is so very small, and is therefore difficult to operate upon, plus the fact that more skin is removed from an infant than from an adult.  This means that excessive skin removal is quite common and this problem can result in painful erections, and also (contrary to popular belief) restrict the growth of the penis at puberty.

Plastibell 

The latest figures I can find for complications caused by circumcision are for the USA, where the rate is given as between 3% and 9% - which doesn't sound like a lot, but actually means tens of thousands of boys suffer from complications because of this surgery.   There are deaths even in such developed countries as Australia, The USA and Canada.   I believe that even ONE baby suffering from complications is one too many, and that a procedure which is unnecessary, and has the risk of death attached should not be carried out.

The frightening thing, from my point of view, is that in many cases there are no figures for death or complications following circumcision.  Many complications are not followed up at the point where the procedure was done, and therefore are not reported.


I checked some statistics at the webcite Circinfo.org, and was appalled to see the following, just from Australia:

1919 Tuberculosis contracted during circumcision
1943 Gangrene following circumcision
1953 "Begg noted that figures for deaths from circumcision were not available, but reported Gairdner's observation (1949) of 16 deaths annually in England and Wales for period 1942-1947 and commented "There was every reason to believe that a proportionate mortality would prevail in Australia".
1965 "Dr R Southby mentioned two neonatal deaths which had resulted from infection after circumcision in the last year, and other instances of surgical complications leading to litigation"
1966 Two deaths from haemorrhage.
1967 Commonwealth Statistician report of one death in 1963 and one in 1964. Statistician commented "Figures of deaths from complications of circumcision for other reasons (other than ritual or preventive) are not available."
1969 Official statistics reported two deaths from 1959 to 1969 but "There is probably no adequate record of morbidity (death)"
1977 Death from meningitis
1993 Death from anaesthetic overdose, Brisbane
And for the complications arising, we have dozens, including tuberculosis following circumcision, septicaemia and also pneumonia in one baby, staphlycoccus in another.  Infection leading to loss of a third of the penis. In 1970 as report of complications at 15.5%.

A letter from A. Clements, MJA in 1972 "Examining large numbers of children at school medical inspections over the last few years I am appalled at the phallic mutilations exhibited by many of these children, some of whom have even been subjected to a subsequent 'tidying up' procedure after being bady mauled in infancy".

Other complications include cases of meningitis, including one fatal, one mildly 'retarded' and one seriously 'retarded';  two Sydney babies suffered severe blood oxygen deprivation after the administration of prilocaine anaesthetic.


And just in case you are thinking this is all past news, and these things don't happen in this modern world, think again!  In 1997 a baby almost bled to death after circumcision, 2006 a doctor was deregistered for ten years by NSW Medical Board for misconduct..including an excessive incidence of circumcision complications.   And in 2010 a Melbourne doctor was suspended for three months (only) after "incompetent circumcision" - using a Plastibell device, resulting in severe injury to the penis and the need for plastic surgery, on a 2 year old boy.

And we have an "enviable record"? 

Other complications include:  meatal stenosis, which is a narrowing of the urethra, this can interfere with urination.  It may require further surgery to remedy.   Adhesions, where the remnants of the foreskin try to heal attached to the head of the penis, in an area where they are not supposed to grow. These adhesions are treated by doctors ripping them open, with no anaesthetic.  Buried penis, where the penis is trapped or buried because too much skin has been removed, forcing the penis inside the body.  Infection is also a serious risk with the prevalence of the modern drug resistant bacteria which can be picked up in the hospitals. 

Regarding the myth that circumcision is necessary to prevent Urinary Tract Infections in infants: 

This is a no-brainer, as research for this claim was based on one study, of babies born in one hospital in 1985.  According to Psychology Today, the study had "many problems, including that it didn't accurately count whether or not the babies were circumcisied, whether they were premature and thus more susceptible to infection in general, whether they were breastfed, whether their foreskins had been forcibly retracted".  This last can introduce bacteria and lead to infection.  Since this 'research'  there have been many further studies, some showing either no decrease in UTI's from circumcision, some showing an actual increase.  The generally accepted figures  state that around 0.188% of circumcised babies and 0.702% of intact babies develop a UTI.  Such a slight difference as this hardly matters.  The incidence for girls of UTI's is around 5%.   Also immediate breastfeeding apparently protects male and female babies from UTI's. 


Tomorrow I will look at the last of the myths I will cover, that of STDs and HIV - I think you will be quite surprised by the most recent findings.  I will also look at the long term and psychological implications of circumcision.  They aren't pretty in a lot of cases.

Sunday, February 19, 2012

Circumcision - I Wouldn't Do It To My Child If You Paid Me - Part Three

A warm welcome back to those of you who are following this story, and thank you for staying with me.   We have looked at the general, simplified anatomy of the penis, and the main ways in which circumcision is performed.  Now I want to dispel a few myths, many of them perpetrated by the medical profession, and to enlighten you about the facts.

There are still staunch advocates for infant circumcision, but it is fact that there is no medical organisation anywhere which recommends this routine circumcision.  The Royal Australasian College of Physicians, The British Medical Association and the American Academy of Paediatrics are included in those organisations.  Routine neonatal circumcision has been declared unlawful in South Africa, Sweden (apart from on religious grounds) and Finland.


A myth still floating around is that doctors advocate routine circumcision of newborn baby boys.  The truth?
The RACP says, in their Policy Statement, in part:  After extensive review of the literature the RACP reaffirms that there is no medical indication for routine neonatal circumcision. The complication rate of neonatal circumcision is reported to be around 1% to 5% and includes local infection, bleeding and damage to the penis. Serious complications such as bleeding, septicaemia and meningitis may occasionally cause death.

The possibility that routine circumcision may contravene human rights has been raised because circumcision is performed on a minor and is without proven medical benefit.
 
Review of the literature in relation to risks and benefits shows there is no evidence of benefit outweighing harm for circumcision as a routine procedure in the neonate.

 
From Wikipedia:
The Royal Dutch Medical Association stated in 2010: "There is currently not a single doctors' organisation that recommends routine circumcision for medical reasons."  The Royal Dutch Medical Association issued a new policy in May 2010: "The official viewpoint of KNMG and other related medical/scientific organisations is that non-therapeutic circumcision of male minors is a violation of children’s rights to autonomy and physical integrity. Contrary to popular belief, circumcision can cause complications – bleeding, infection, urethral stricture and panic attacks are particularly common. KNMG is therefore urging a strong policy of deterrence. KNMG is calling upon doctors to actively and insistently inform parents who are considering the procedure of the absence of medical benefits and the danger of complications."
 
The Fetus and Newborn Committee of the Canadian Paediatric Society posted "Circumcision: Information for Parents" in November 2004, and "Neonatal circumcision revisited" in 1996. The 1996 position statement says that "circumcision of newborns should not be routinely performed", and the 2004 advice to parents says it "does not recommend circumcision for newborn boys. Many paediatricians no longer perform circumcisions."
 
The British Medical Association's position (June 2006) was that male circumcision for medical purposes should only be used where less invasive procedures are either unavailable or not as effective. The BMA specifically refrained from issuing a policy regarding “non-therapeutic circumcision,” stating that as a general rule, it “believes that parents should be entitled to make choices about how best to promote their children’s interests, and it is for society to decide what limits should be imposed on parental choices.”
 
The American Academy of Pediatrics (1999) found both potential benefits and risks in infant circumcision, however, there was insufficient data to recommend routine neonatal circumcision. In situations involving potential benefits and risks, and no immediate urgency, they state that "parents should determine what is in the best interest of the child". They continue, "To make an informed choice, parents of all male infants should be given accurate and unbiased information and be provided the opportunity to discuss this decision." They said, "In the pluralistic society of the United States in which parents are afforded wide authority for determining what constitutes appropriate child-rearing and child welfare, it is legitimate for the parents to take into account cultural, religious, and ethnic traditions, in addition to medical factors, when making this choice." If a decision to circumcise is made, the AAP recommend using analgesia to reduce pain, and also said that circumcision on newborns should be performed only if they are stable and healthy.

 
The American Medical Association (1999) noted that medical associations in the US, Australia, and Canada did not recommend routine circumcision of newborns. It supported the general principles of the 1999 Circumcision Policy Statement of the American Academy of Pediatrics.
 
The American Academy of Family Physicians (January 2007) acknowledges the controversy surrounding circumcision and recommends that physicians discuss the potential harms and benefits of circumcision with all parents or legal guardians considering circumcision for newborn boys.

 
The American Urological Association (May 2007) states there are benefits and risks to circumcision, recommending that circumcision "should be presented as an option for health benefits" while acknowledging that "evidence associating neonatal circumcision with reduced incidence of sexually transmitted diseases is conflicting." It feels that parents should consider medical benefits and risks, and ethnic, cultural, etc. factors when making this decision.
 
So medical authorities are agreed that there are medical risks, and that routine circumcision of newborns should NOT be performed.  It is the old saying "if it ain't broke, don't fix it".   So much for the advocates.

Note that there is still no mention of the male having the right to make decisions about his own body?


A second myth is that it is less painful for circumcision to be carried out when the boy is a baby, rather than later in life.
 
Circumcision is extremely painful - and traumatic - for a baby. Just being strapped down is frightening for a baby. The often repeated statement that babies can't feel pain is not true. Babies are as sensitive to pain as anyone else. Most babies scream frantically when their foreskin is cut off. Some defecate. Some lapse into a coma. The reason some babies don't cry when they are circumcised, is that they can't cry because they are in a state of shock. Most babies are circumcised without anaesthesia. Anaesthetics injected into the penis don't always work. Being stuck with a needle in the penis is itself painful for a baby, just as if would be for anyone else. Babies are rarely given pain medication right after they are circumcised or during the week to ten days it takes for the wound to heal. Pain medication is not always effective and is never 100% effective. (Nocirc.org)

 
In 1997, doctors in Canada did a study to see what type of anaesthesia was most effective in relieving the pain of circumcision.  As with any study, they needed a control group that received no anaesthesia.  The doctors quickly realized that the babies who were not anaesthetized were in so much pain that it would be unethical to continue with the study.  Even the best commonly available method of pain relief studied, the dorsal penile nerve block, did not block all the babies' pain.  Some of the babies in the study were in such pain that they began choking and one even had a seizure  (Lander 1997). (Psychologytoday)
 
Tiny infants experience the most excruciating pain, both during circumcision and for weeks following the procedure.  They can exhibit changes in behaviour, for example avoiding physical contact, sleep disturbances, frequent crying and even reluctance to breast feed.
The last myth today (but not the last myth of all) is that of anaesthetics being used for newborns.

 
Most newborns do not receive adequate anaesthesia.  Only 45% of doctors who do circumcisions use any anaesthesia at all.  Obstetricians perform 70% of circumcisions and are least likely to use anaesthesia - only 25% do.  The most common reasons why they don't?  They didn't think the procedure warranted it, and it takes too long  (Stang 1998).  A circumcision with adequate anaesthesia takes a half-hour - if they brought your baby back sooner, he was in severe pain during the surgery. (Psychologytoday)
 
Oh, before I go any further, there is a doctor (who shall remain nameless) here in Australia who happily chops off foreskin from babies willy-nilly and has a huge website in favour of circumcision.  In my opinion he is a sadist, but he would probably dispute this. He also advocates the use of the EMLA patch.  There have been many very adverse results from the EMLA patch, and the reason is very very simple:
 
The following is from www.cirp.org:
 
THE CIRCUMCISION REFERENCE LIBRARY

EMLA topical anaesthetic for neonatal circumcision


This page presents information about risks associated with the use of EMLA cream for relief of infant circumcision pain. Although certain pediatric groups recommend its use, other authorities tell a different story.
"EMLA Cream is not recommended for use on mucous membranes because limited studies show much greater absortion of lidocaine and prilocaine than through intact skin. Safe dosing recommendations for use on mucous membranes cannot be made because it has not been studied accurately."
"EMLA Cream should not be used in infants under the age of one month, nor in infants under the age of twelve months, who are receiving treatment with methemoglobin-inducing agents (see Methemoglobinemia subsection of WARNINGS).


EMLA has added a new warning to their product inserts and their web site. The new warning states:
"EMLA Cream is not recommended for use prior to circumcision in pediatric patients."
and also:
The Canadian Nurse, August 1994, pp. 5-6
[Material in brackets added. CIRP]
Editor's note: Recently we received a copy of the following letter from Grace Boudreau, RN, Director of Quality Assurance, G. R. Baker Memorial Hospital, Quesnel, B.C. [British Columbia, Canada]. The letter was sent to all general practitioners, hospitals and pharmacies in Northern British Columbia on March 28, 1994. We have permission from the letter's author, Dr. Marie Hay, to print the letter in its entirety (bold type represents emphasis expressed in original letter.)


Dear Doctor,
The Department of Paediatrics at Prince George Regional Hospital recently discussed the unfortunate case of a 21-day-old male child who was circumcised using Prilocaine as a local anesthetic agent. A few hours after the circumcision the baby developed significant Methaemoglobinaemia [reaction with the blood] due to the Prilocaine anesthetic.
The department of Paediatrics is issuing a strong warning to all physicians who perform circumcisions. We strongly advise that Prilocaine local anesthetic not be used under any circumstances for neonatal circumcision. It is also interesting to note that EMLA cream contains 2.5% Prilocaine. It also therefore should not be used on the mucous membranes of newborns when they are circumcised.
It is the Department of Paediatrics' recommendation that no infant under the age of 3 months gets Prilocaine or EMLA cream in any form because of the serious risk of Methaemoglobinaemia.
I understand from speaking with an Intensivist at B.C. Children's Hospital that two other cases of Methaemoglobinaemia due to Prilocaine have also been noted in B.C. in the past recent months. As you know Methaemoglobinaemia can cause brain damage and death in small infants.
 
Even the dorsal penile nerve block leaves the underside of the penis able to feel pain. Babies go into shock, and although this appears that they are quiet,  it  is their  body's  reaction  to  profound  pain  and distress.  Nurses will tell the parents "he slept right through it" so as not to upset them. Who would want to hear that their baby was screaming throughout in agony?
 
There are many risks involved with using anaesthetic on newborns, the above are just a small example of the outcome of using  EMLA (which by the way is NOT sterile) and prilocaine - which EMLA contains. 
 
More myth busting tomorrow night.

Saturday, February 18, 2012

Circumcision - I Wouldn't Do It To My Child If You Paid Me To - PART TWO

Thanks for sticking with me on this, and for reading what I have put up so far.  It is a bit of a rugged road, and a most controversial subject.  My thought on this is that there are millions out there who are not fully informed about the whole subject of circumcision.  So here we go, on our road to information, part two.

There are several main methods which are used to circumcise an infant, and remember I am not talking about places like Africa where there is no real hygiene and they carry out mass circumcision - with dire results.

A warning if you are squeamish - some of the pictures are graphic.

The first one I will talk about is the straight out cutting method.  This is probably having  its death knell sounded, although religious practices still seem to require this method.  There really doesn't seem to be a standard for which method of circumcision is used, although some countries prefer the Plastibell and some the Gomco Clamp. 

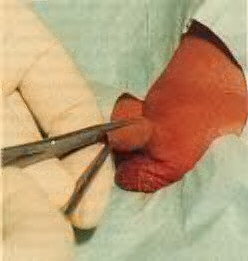
The so-called "simplest" method appears to have varied little from the "traditional" operation.  The foreskin is pulled forwards and gripped in a pair of clamping or crushing forceps, which are placed at an angle to match the slope of the back of the glans.  The skin is cut off in front of the blades of the forceps, then the inner skin is pushed back and fastened, with  stitches, to the outer skin on the shaft. In infants, the stitches are often not used. Their main purpose is to close off blood vessels, and crushing with the forceps is often enough to accomplish this.   How complete the circumcision is depends upon how hard the skin is pulled forward before  clamping. Making the cut while the skin is pulled over the glans provides a safeguard against removing too much. Much of the inner skin remains, so the scar, after healing, will be well down the shaft. It is usually rather irregular but very inconspicuous.
NO ANAESTHETIC CAN BE USED
Lidocaine is used. Note it is for after the operation. According to several nurses at University of Michigan, it does very little or nothing to alleviate the pain of circumcision.

Betadine is used to swab the penis and scrotum to help prevent infection
The foreskin is sealed down to the penile head and must be torn off in order to be retracted in infancy.

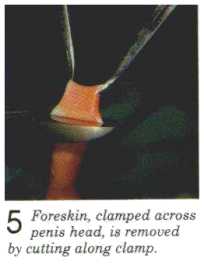
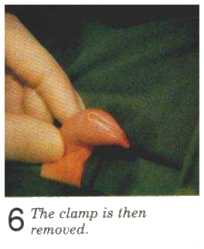
The foreskin is pulled up, clamped for several minutes to prevent excess bleeding, and cut along the clamp with a scalpel.
What you see is not foreskin, but skin from the shaft of the penis. The edges stick together because they are still "raw".

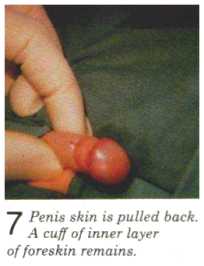
The distinction between shaft skin and where the foreskin was cut away is obvious. The part of the foreskin that used to touch the glans ("inner foreskin") is what is between the shaft skin and the penile head in the picture
Excessive bleeding is the most common complication of infant circumcision.

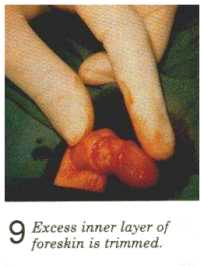
After the inner foreskin is removed, notice that half the shaft skin has been cut away-- altogether,about 2/3 of all the skin of the penis.
The remaining shaft skin is pulled up to meet the glans and attached with stitching.

The penis now has 1/3 to 1/2 less penile skin to accommodate erections and the glans is permanently exposed. The glans will lose its shininess and dark red coloring as the site heals within the next week or so. What was before an internal part of the body, is now external and it will grow a sort of callous over the glans as part of the healing process.
 Pictures from http://www.circumcisionquotes.com/magcirc.html


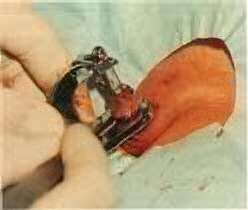
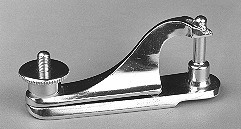
The Gomco Clamp, is an invention of Hiran Yelland and Aaron Goldstein, from 1934.  It is reported to be based on the tyre lever used for Model T Ford cars.  It is a metal ball, and a flat plate with a hole in it placed over both, to define the position.  These are brought together by a screw and apply circular crush and fusing force - of between 8,000lbs to 20,000lbs.
Circumcision with the Gomco clamp and the Plastibell device have many of the same features. The foreskin is grasped with two mosquito clamps at the 10 o'clock and 2 o'clock positions These clamps are used to hold the foreskin up. A third mosquito clamp is used as a probe to destroy any adhesions under the foreskin from the 8 o'clock to the 4 o'clock positions and is then clamped about 2/3rd of the way between the foreskin opening and the corona. This action creates the crushed area for the dorsal slit. The third clamp remains in place for one minute. The dorsal slit is then cut through the middle of the crushed area, using tissue scissors. The foreskin is peeled back, and any additional adhesions are destroyed using a blunt probe. 


The Gomco clamp was designed to crush about 1 mm of the foreskin around the circumference, while the Gomco bell protects the head of the penis from injury during removal of the foreskin. The bell is placed inside the foreskin, and the dorsal slit is secured over the bell with a sterile safety pin. This allows the handle of the bell to pass through the circular opening of the clamp, without the foreskin slipping out. The foreskin can be brought through the opening by grasping it with sterile gauze. The thumbscrew is tightened until snug, and the visible foreskin is removed using a scalpel blade distal to the junction of the bell and the clamp.  The clamp should remain secure for a total of five minutes, to allow the crush effect to be complete. This step is designed to reduce the incidence of bleeding after the clamp is removed.

Gomco Clamp

When the thumbscrew is loosened and the bell gently removed from the clamp, the foreskin will stick to the bell because of the crushing. The foreskin can be loosened by gently peeling with a gauze swab to liberate the glans and show the final result. The edge of the foreskin and the corona of the penis are then gently wrapped in precut petrolatum gauze, which remains in place for 12 to 24 hours.
 
The Plastibell is designed to cause circumcision by cutting off the blood supply to the end of the foreskin. Dead tissue falls off 7 to 12 days after the operation. No advantages of the Plastibell technique over other techniques have been documented, except "ease of use." Some studies have shown a small increase in the incidence of infection with the Plastibell device.


Ensuring that the correct size of the Plastibell is used is important. (N.B This is done by trial of different sizes) A fit too small can cause tissue strangulation and necrosis, and one too large may result in too much foreskin being removed and the penis being denuded of skin. After making the dorsal slit as outlined for the Gomco technique, the Plastibell device is placed on the glans and the cut foreskin is pulled over the top of it. 
The cut foreskin is brought over the top of the Plastibell until the tip of the incision is above the string placement guide on the device. The foreskin is clamped across the top of the Plastibell with a straight clamp. The string is placed around the foreskin and the Plastibell device in a groove that acts as a placement guide. The string is then tightened and tied in a simple square knot. An adequate result is obtained when the skin just distal to the string blanches without the string breaking. The excess foreskin is trimmed from around the bell using iris scissors . The handle is then broken off the device. 

Plastibell device
 
The Mogen Clamp - A blunt-edged probe is used to separate the glans from the preputial lining, taking care not to traumatize the frenulum. The prepuce is lifted upward and outward by the hemostat. This action causes the glans to retract towards the scrotum, preventing accidental amputation of the glans. The open jaws of the Mogen clamp are placed around the prepuce (grooved side facing the glans) as it is lifted upward.  The clamp is closed for one to one and one-half minutes. If the infant is more than six months old, the clamp should remain closed for five minutes.

Mogen Clamp

While the clamp is closed, the prepuce is cut away distal to the clamp. The clamp is then opened slowly and removed. Downward pressure is applied to the  skin around the corona, until the skin-mucosal seal is broken and the glans is liberated.  A blunt probe is used to remove any additional adhesions. Petrolatum gauze is applied to cover the operative site. The preputial skin around the corona of the glans will often have a "dog-eared" or asymmetric appearance. As the infant grows, this aspect becomes less prominent.
There are other methods used, e.g. the Tara Clamp, the SmartKlamp.  I believe the above will give you a fair idea of the procedure, without going into further clamp details.


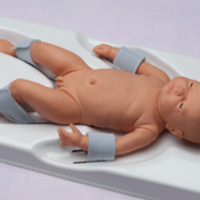
Of course, the infant has to be restrained, and lo! there are manufacturers who have come up with the perfect solution.  One of these if Olympic Medica's very own 
 
Infant Immobilizer Circumstraint. Fast immobilization of newborns 4-16 lbs. Use during circumcision, transfusion, minor surgery, x-ray. Complete with four adjustable Velcro straps for securing arms and legs.
"In less than 30 seconds, a nurse can immobilize the struggling infant securely in the correct position with Circumstraint. It works on a proven principle of positive 4-point restraint. Soft wide Velcro straps encircle the infants elbows and knees, depriving him/her of leverage. "

 
"Circumstraint's comfortable contoured shape positions the infant, hips elevated, perfectly presenting the genitalia."
 
"He's held safely and securely without danger of escape."
 
"Always a fast, easy means of immobilizing newborns for circumcision..."
 
And the Stang

This light weight chair positions the infant comfortably while providing surgical access the the operative site."
"Newborn pain management is an issue of concern to many health care professionals today." 
"Any physician or nurse who has attempted to extend the arms and legs of a term neonate to strap him into a rigid restraint, realizes the resistance to extension that all neonates possess.

Positioning of the baby in the Circ Chair allows the infant to sit with his hips abducted and flexed, knees flexed, and head elevated at various positions up to 30-45 degrees. Soft velcro straps adjust to the baby's size. The instrument platform is designed to accommodate commonly used circumcision clamps."


The patient cannot understand, consent, refuse or escape.


And the 'struggling infant'  - hmm.  No anaesthetic.  Which I will cover in my next part of this blog, Part Three.


Friday, February 17, 2012

Circumcision - I Wouldn't Do It To My Child If You Paid Me


This will be a series of blogs, I hope you will read them all, and that I will be able to explain many things of which you may not have been aware. 

A young friend asked if I would do a blog about circumcision.  In my complete ignorance I replied "of course!"  Little did I realise what was in store.  This blog has been months in the making, and has given me more nightmares, tears and headaches than I anticipated.   The debate amongst the medical fraternity about male circumcision runs hot and furious. 

As a layperson I looked at what statistics are quoted, anecdotal evidence presented, and reams of learned submissions online.  And at the end of it all my heart says the same as it did before I started.  I do NOT believe in male circumcision.  At all.  Reading of the complications (many of them hidden - more on this later) and of the deaths and mutilations from 'routine' circumcision has made me feel ill, and made me weep.  This is just in USA and Australia, not in somewhere like Africa.

My friend actually pointed me to a very informed blog (anti-circumcision) and for a moment I was quite disheartened.  The blog said many of the things I had planned, quoted similar statistics and the like.  When I stepped back for a minute it occurred to me that this is a 'so what?' situation.  My voice can be heard as well, and if we are on the same side, all the better!

I do understand that circumcision has been undertaken for religious and cultural reasons for thousands of years and is an important ritual in some religious and cultural groups. It was interesting to see that there is actually a movement amongst member of the Jewish religion, to stop circumcision of their young boys.

In Australia and New Zealand, thankfully, the rate of circumcision has recently declined, and it is estimated by the RACP (The Royal Australasian College of Physicians) that  in 2010, ten to twenty percent of newborn male infants were circumcised.  This is, thankfully, a much lower percentage than, for example, in the 1960's, when there were 70% of boys circumcised.

There is a growing public movement against female genital mutilation, which has many prominent  figures (including the model Waris Dirie)speaking out, making films, media appearances etc.  Why then is it fine, and apparently largely accepted to perform male genital mutilation? This is what it amounts to, and I don't see how anyone can argue their way around that.  The male foreskin is there for a reason, no?  Else why would men be born with a foreskin?  Women have the labia, which is like our own foreskin - and there for a specific reason.  The scarring caused by circumcision is not just physical either.  There are serious psychological problems in many men who have been forcibly circumcised.

I say forcibly deliberately - circumcision of  a neonate, or a young boy equates to a serious breach of human rights, and to me is totally unethical.  If a child is too young to be given the right to consent in a case of non-therapeutic surgery then that surgery should not be carried out.

Reasons parents have given for having their baby circumcised vary from "it is healthier"  and "it is cleaner" to something along the lines of "all the other men in the family are circumcised" - and similar.  Very few of them seemed to be informed beforehand of the dangers associated with circumcision, and many of them were told something along the lines of "it's only a little snip and it's done".  NOT SO.

In Australia, we apparently followed the lead of England and the USA, where doctors, in the Victorian era of prudery, espoused the belief that circumcision, hysterectomy and clitoridectomy (removal of the clitoris)would prevent or cure various illnesses.  These included masturbation, mental illness and tuberculosis among others.  There was, however, a dissenting group of British doctors, and in 1867 circumcision of females was banned.  At this time it was recognised that it was a woman's right to make decisions about her own body.  Male circumcision continued into the 1900's, with physicians misguidedly believing that both sexes could thereby be protected from sexually transmitted diseases, and cancer, and that all cases of phimosis in male infants made circumcision necessary. When will we recognise that it is a man's right to make decisions about his own body?

 
Before I go further I will just put in a little about the foreskin, and the penis, so that we understand the full horror of what is done to the baby during circumcision. 

Simply put : The foreskin covers the tip of the penis, or the glans. It extends from the skin that covers the shaft of the penis, and it has a thinner and more sensitive inner surface.  This inner surface is attached to the shaft of the penis where it joins the glans.  The foreskin protects the inner surface as well as the tip of the penis. Under the foreskin,  the skin of the glans is moist, and thin. At birth it is normal for the the inner layer of the foreskin to be attached to the glans.  The foreskin cannot be retracted (pulled back) at this age. There is a very sensitive band of tissue called the frenulum which connects the inner foreskin to the glans,  under the penis.  This is often referred to as the male G-spot. As a boy grows, the inner skin separates and the opening becomes more elastic, so that by the time he is grown, he should be able to retract it without discomfort.  This separation can occur at between 3 to 13 years of age. 

From Circumcision Reference Library

The foreskin (prepuce) has a sheath of smooth muscle tissue inside the skin which is called the peripenic muscle. The muscle fibres are arranged in a whorl at the end of the foreskin to form a sphincter. The muscle fibers keep the foreskin snugly against the glans penis. The outer surface of the prepuce is skin, however the inner surface is mucosal membrane although it resembles skin in appearance. There is a muco-cutaneous boundary just inside the tip of the prepuce. The prepuce normally covers the glans penis and protects it from foreign matter, friction, drying, and injury.

The prepuce is usually tethered at the bottom by the frenulum. The frenulum's function is to provide pleasure by stretching during sexual intercourse. In fact, the frenulum is colloquially known as the "sex nerve" in France and perhaps throughout Europe. By destroying this stretching action, circumcision completely destroys this fundamental means of sexual pleasure in the human male. There is a hypothesis that stretching of the frenulum during intercourse provides stimulus for ejaculation.

As with other neurologic structures such as the brain, the tip of the prepuce is richly supplied with blood by important vascular structures. The glans penis receives blood through the frenular artery. The prepuce serves as a conduit for several important veins. Circumcision may contribute to erectile dysfunction by destroying these blood conduits.

The prepuce is naturally equipped with several defenses against infection. The infant prepuce has a pronounced tight tip with a sphincter formed by the whorl of muscle tissue that stays closed to keep out foreign matter but opens to allow the outflow of urine. The sub-preputial wetness contains lyzosyme, a secretion that acts to destroy harmful microorganisms. The prepuce contains Langerhans cells which may provide resistance to HIV infection.

The prepuce is profusely innervated (has many nerves) especially near the tip in the ridged band area where the muco-cutaneous boundary occurs. It is now understood that this junction is the most sensitive and erogenous part of the penis.   The accumulation of sensation triggers the ejaculation reflex. Diminution of the available nerve supply would make achievement of orgasm more difficult. 

The ridged band is located near the tip of the prepuce on the inner layer of the foreskin near the muco-cutanaeous boundary. The ridged band merges smoothly with the frenulum. Taylor states that the ridged band is sensitive to motion. The foreskin slides back and forth over the glans during foreplay and intercourse. Typically, the ridged band area of the prepuce is stretched when it passes over the glans penis and, by this stretching action, the multitude of pleasure sensors in Taylor's ridged band are stimulated.
 
The ridged band area, which is stimulated by motion, is the most highly innervated and pleasure producing region of the prepuce. They clearly have an important, but not yet well understood, function in human sexual response.
 
The prepuce of the typical complete male may protect the corona from direct stimulation during intercourse and so tends to prevent premature and unwanted ejaculation. 
 
Other primates. Cold and McGrath described the variations in the prepuce between human males and females and other primate species, concluding from an evolutionary perspective that the prepuce is highly evolved and has a specialized function in each species.
In summary, the prepuce is a unique specialized structure with important immunological, protective, mechanical, erogenous, and sexual functions. The prepuce is essential to normal copulation.
 
The word "circumcision" comes from the Latin circumcisione, from circum (meaning "around") and cædere (meaning "to cut").

In  infants, circumcision is an operation which involves tearing the foreskin away from the glans of the penis,  then cutting along the top of the foreskin,  clamping the foreskin, and cutting it off.  The amount of foreskin removed from one circumcision to the next can be very different, and no two circumcisions are the same, as the skin of the penis is movable, a sheath with no clear indicator as to where it should be cut.

The amount of skin to be removed is estimated.

The next blog will be about the methods used to circumcise a baby boy.